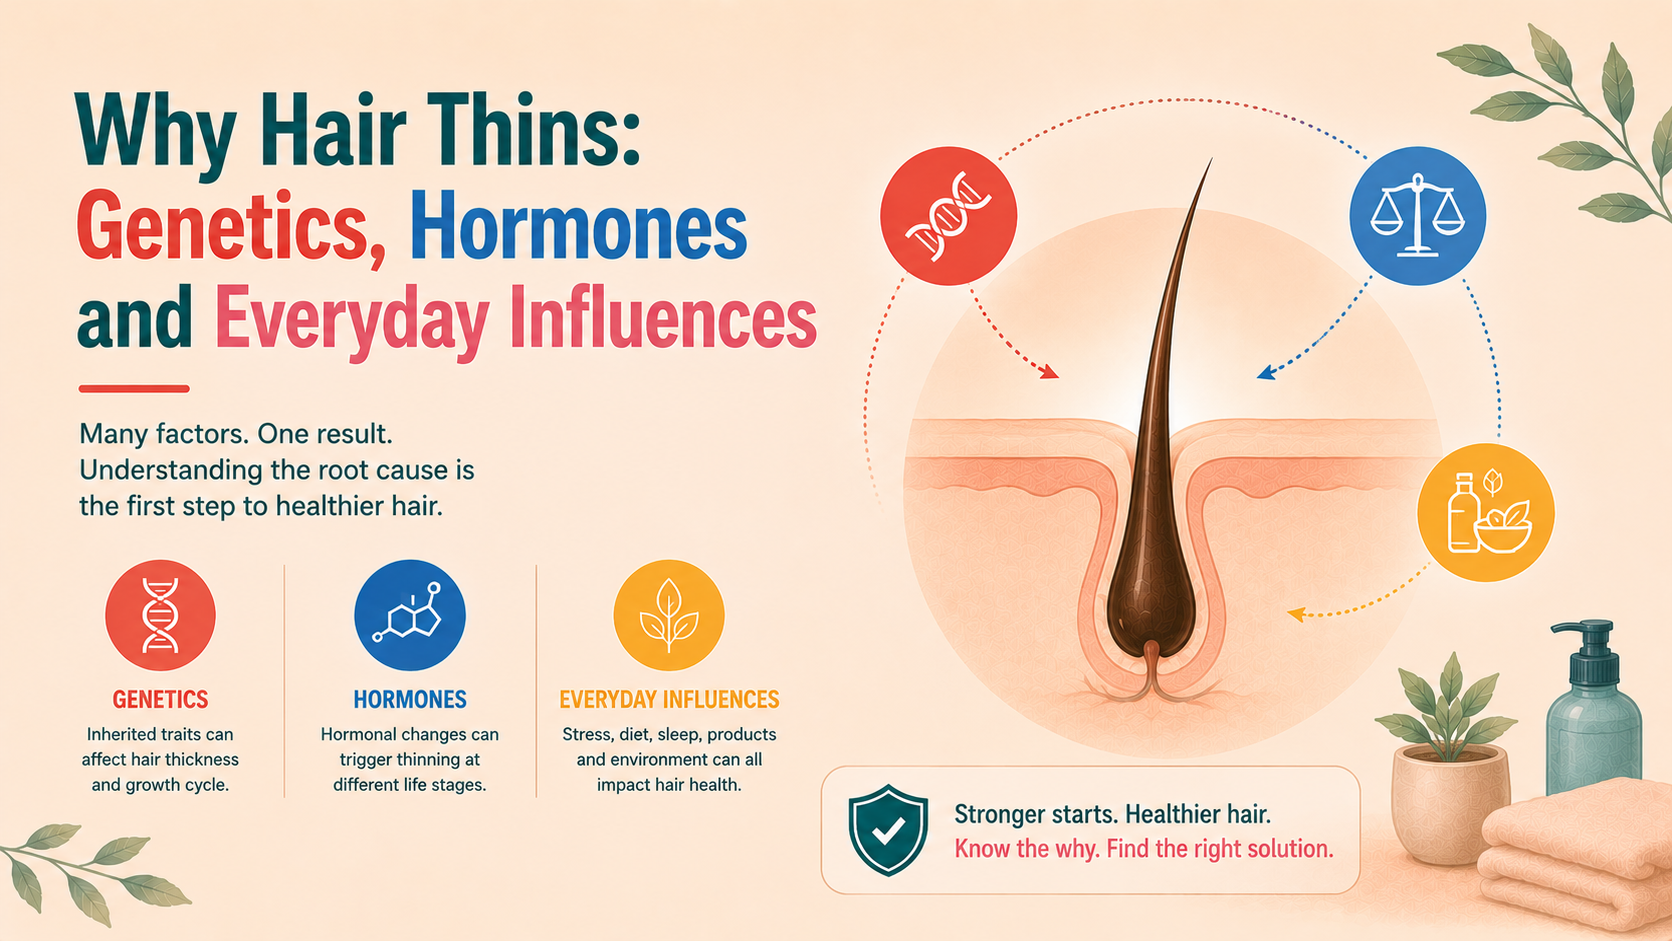
Before choosing a treatment, it helps to understand what is changing in your scalp. I explain how follicles grow hair, why they can produce thinner strands, and why different causes of hair loss need different care.

People often encounter hair loss treatments before receiving a clear explanation of hair loss itself. That makes it harder to judge why a tablet, a lotion or a procedure might help.
I think the biology is a useful place to start. You do not need to memorise every structure in the scalp. You need a picture of how hair normally grows and what can change when it begins to thin.
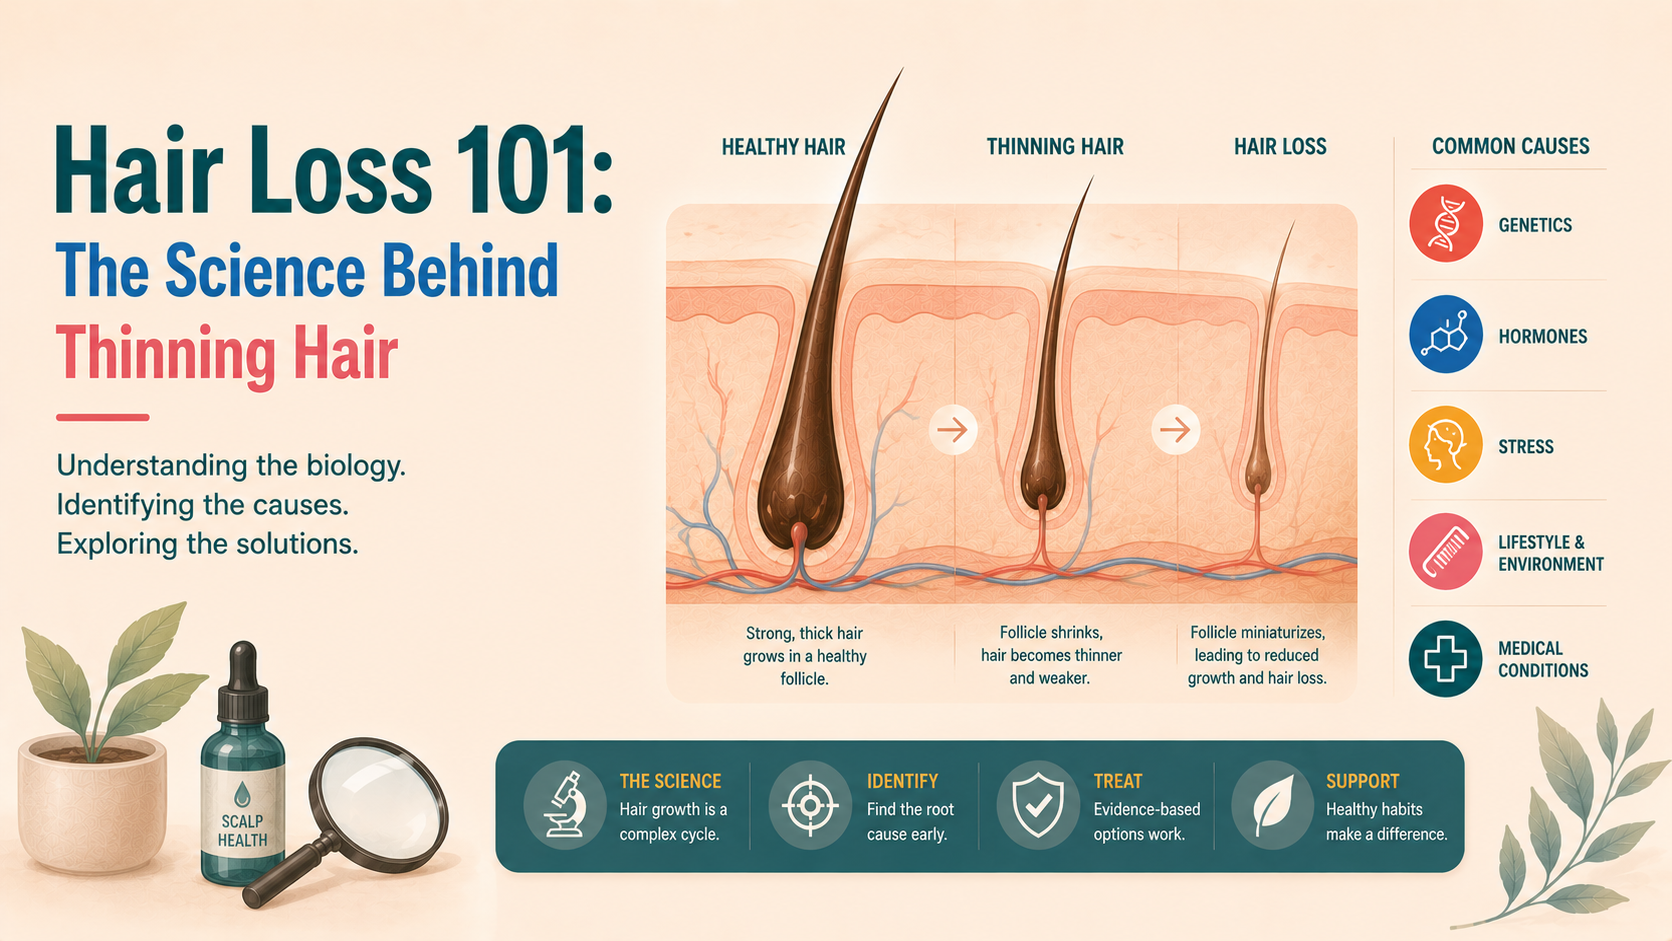
The hair you can see is the product. The follicle beneath the skin is the living structure that produces it. Losing a strand does not necessarily mean losing the ability to grow another one.
At the base of a growing follicle is the hair bulb. Rapidly dividing cells here contribute to the hair shaft, which is largely made of keratin. Within the bulb, specialised cells in the dermal papilla exchange signals with the surrounding cells and help regulate growth.
In my biology video, I describe the dermal papilla as a control centre. That is a useful image, provided it is not taken too literally: hair growth depends on interactions across the follicle and surrounding skin, rather than one isolated switch.
Higher up, a sebaceous gland supplies oil to the hair and skin. A small muscle attached to the follicle produces goosebumps. Scalp hairs often grow in small groups called follicular units, a feature that becomes relevant in transplantation.
Visible fullness depends on more than the number of hairs. Their thickness, curl, colour and arrangement also affect how much scalp you see.
A follicle does not grow a strand indefinitely. During anagen, the growth phase, it actively produces hair. On the scalp this can last years. Catagen is a shorter transition as the lower follicle regresses, followed by telogen, a resting phase.
Exogen describes the release of the old hair. Shedding and the start of another growth cycle are related processes, but they do not operate as a perfectly synchronised four-step clock across your whole scalp.
Most follicles are growing while others are resting or shedding. That staggered timing helps maintain coverage. Finding hairs in the shower is therefore normal; what matters is whether the amount, pattern or appearance of your hair is changing over time.
In pattern hair loss, affected follicles gradually become smaller and produce finer, shorter hairs. This is called miniaturisation. A hair can be replaced without being replaced by one that gives the same coverage.
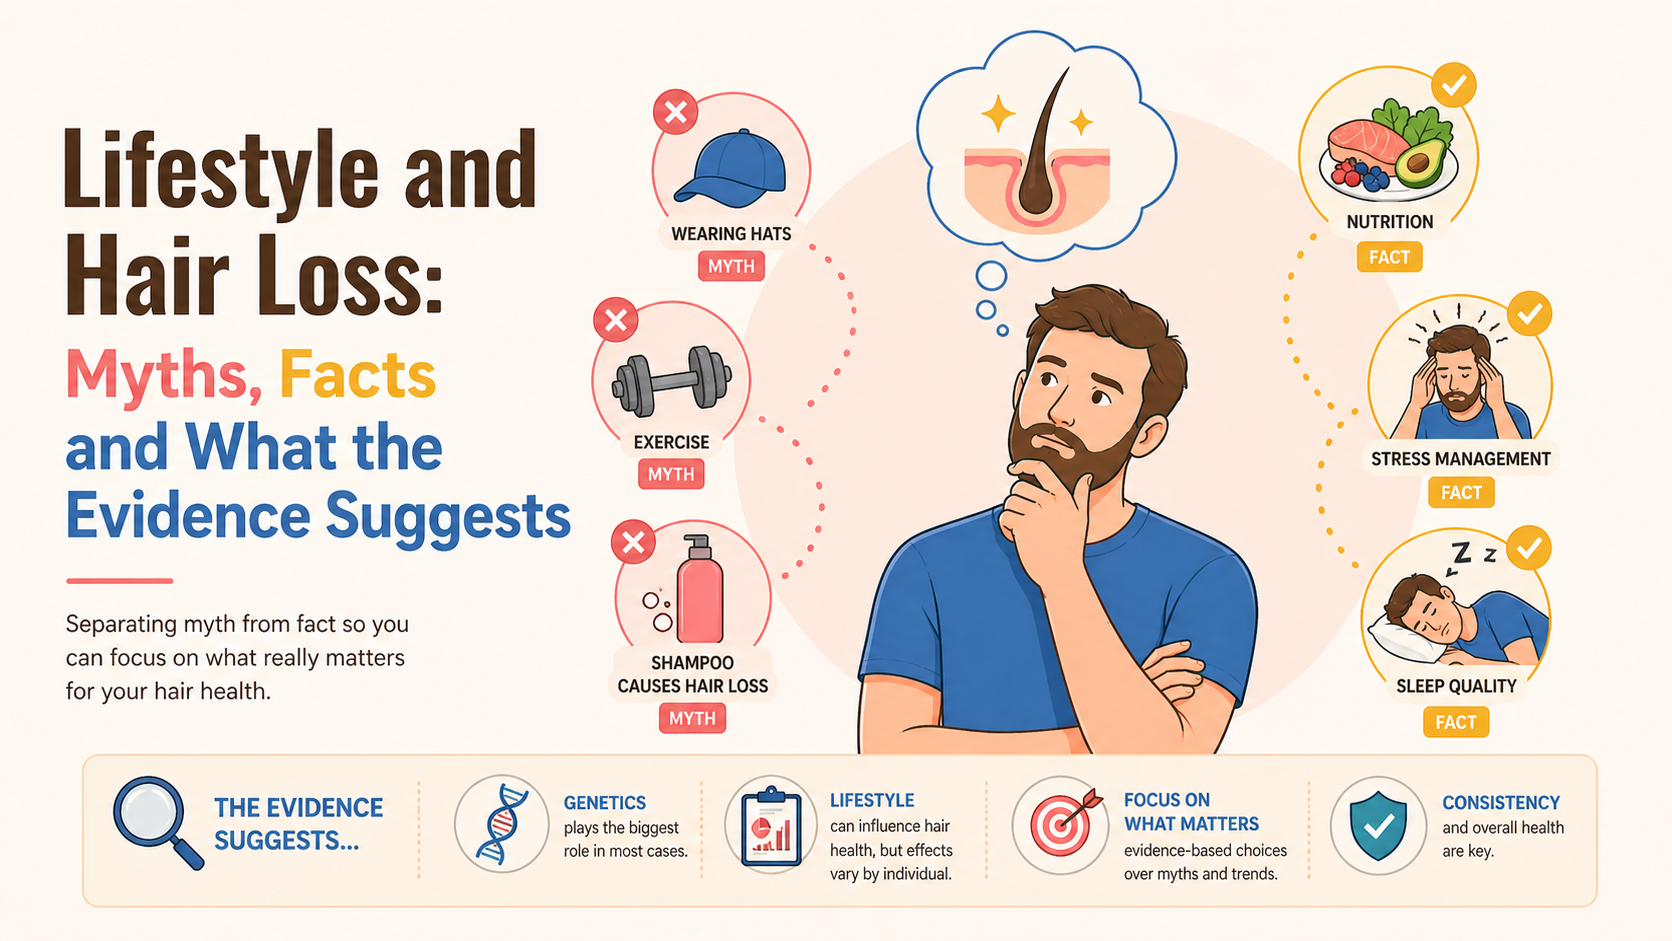
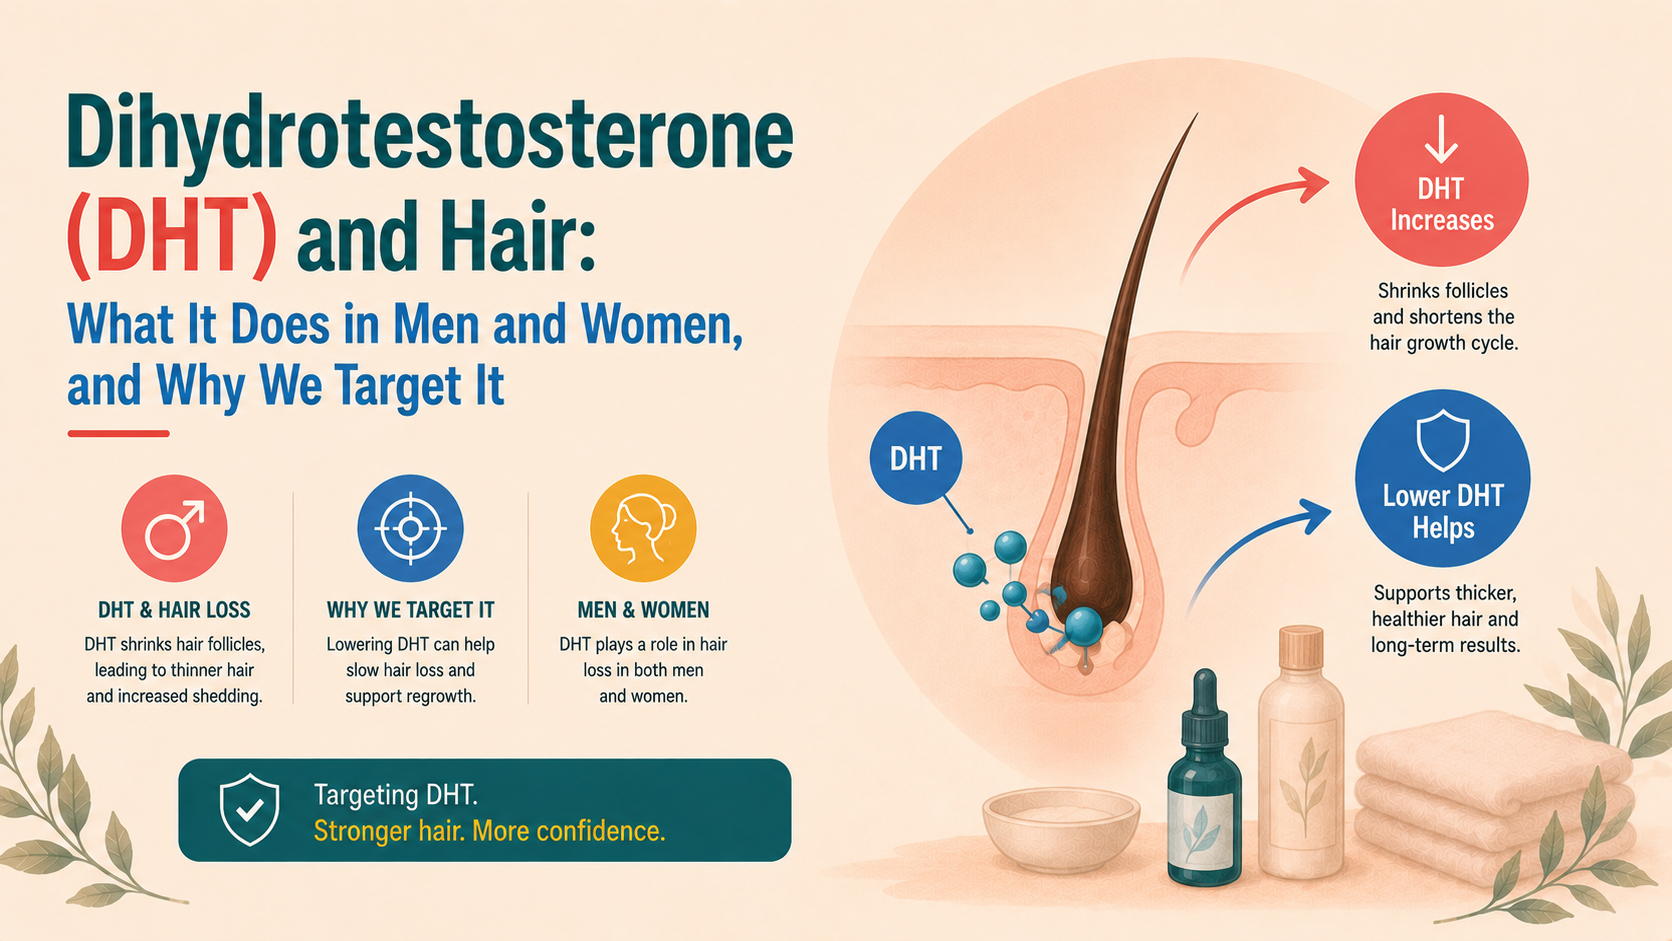
In men, thinning commonly affects the temples, front and crown. Dihydrotestosterone, or DHT, is an important driver in genetically susceptible follicles. Having pattern hair loss does not necessarily mean that the amount of testosterone in the blood is unusually high.
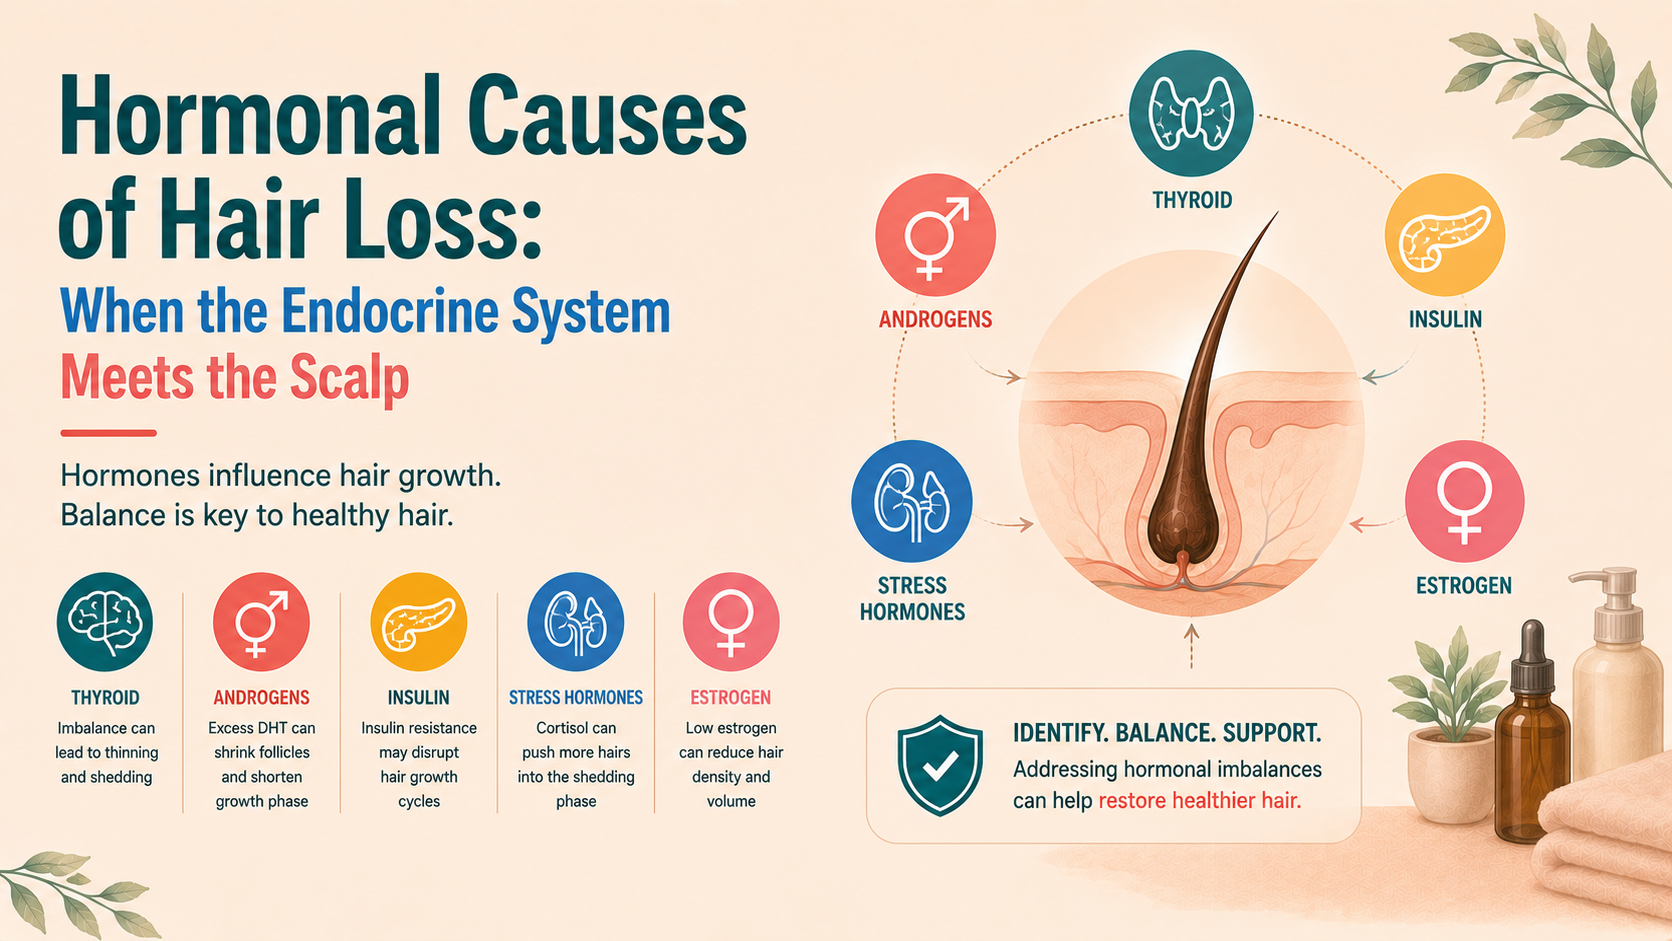
Women often notice widening of the parting or reduced density through the central scalp. Miniaturisation is also a feature, but the contribution of androgens is less straightforward than in male pattern hair loss. Many women have normal androgen levels, and the condition should not automatically be reduced to “too much DHT”.
The process can develop without a dramatic increase in visible shedding. The important change is the quality and size of the hair being produced over successive cycles.
Telogen effluvium occurs when a larger proportion of hairs move out of active growth and later shed. It may follow illness, childbirth, substantial weight loss or another trigger, often with a delay of a few months. The follicle is usually preserved, so recovery is possible, although identifying a trigger does not rule out another condition alongside it.
In alopecia areata, immune activity disrupts hair growth. It often produces smooth patches, but can cause more extensive or diffuse loss. It needs a different assessment from ordinary pattern thinning.
Traction from tight hairstyles can damage hair and follicles. Repeated hair pulling is another distinct cause that deserves support rather than blame.
Scarring alopecias, including lichen planopilaris, can permanently destroy follicles. Treatment aims to control active disease and protect the hair that remains. Regrowth from an already destroyed follicle is not expected.
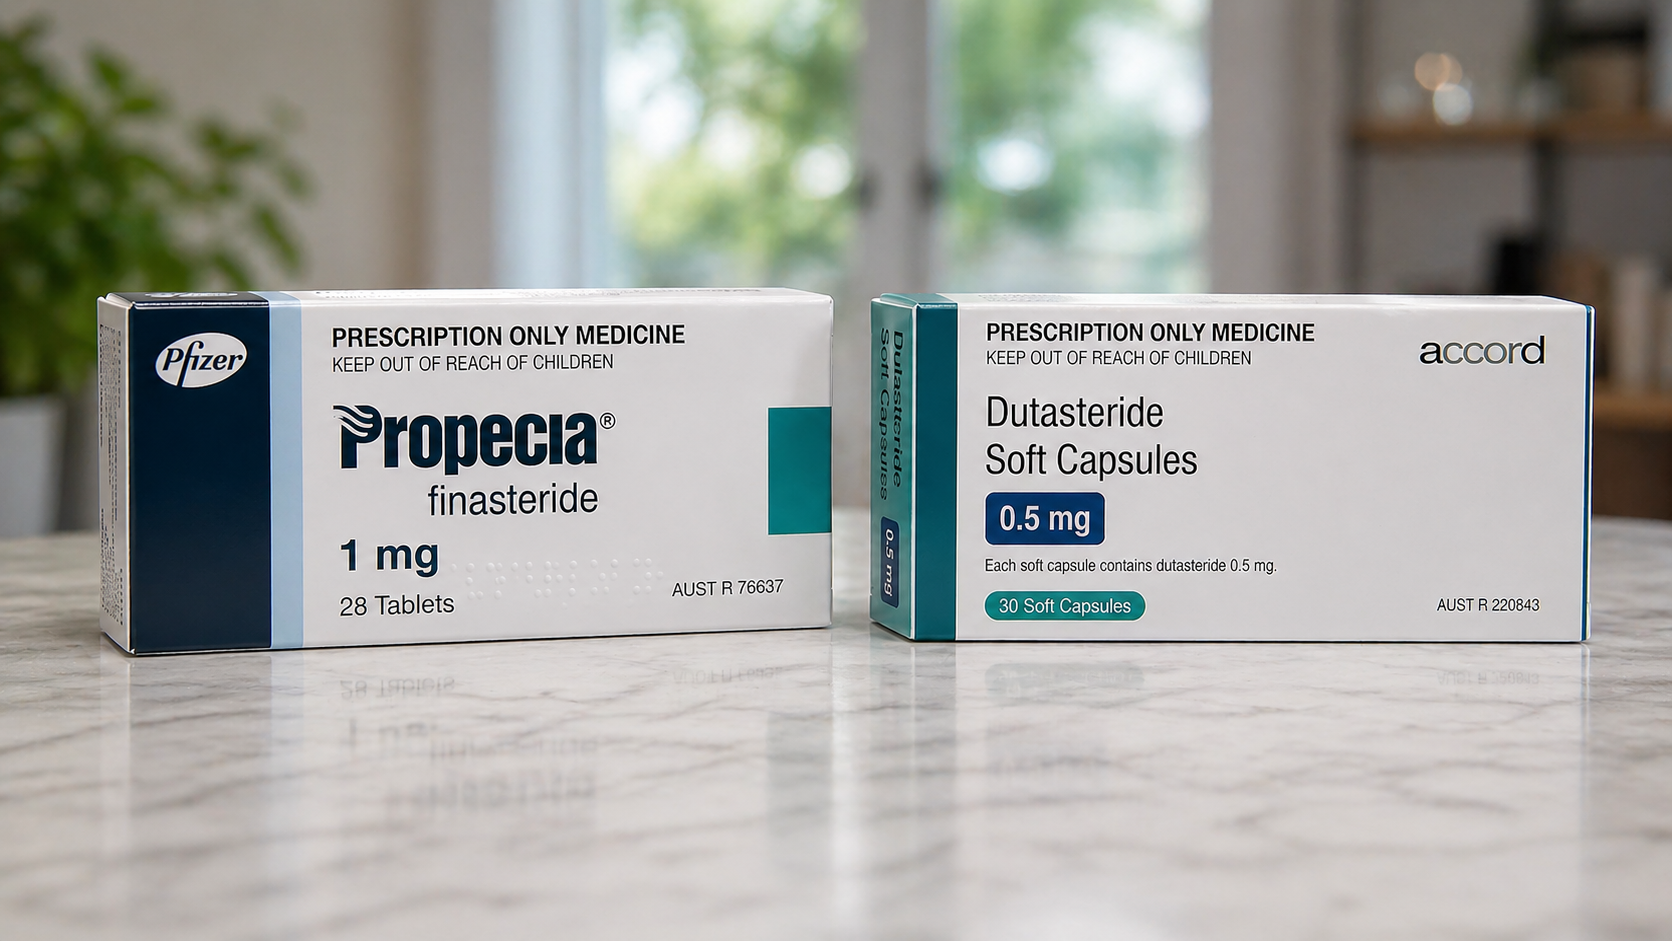
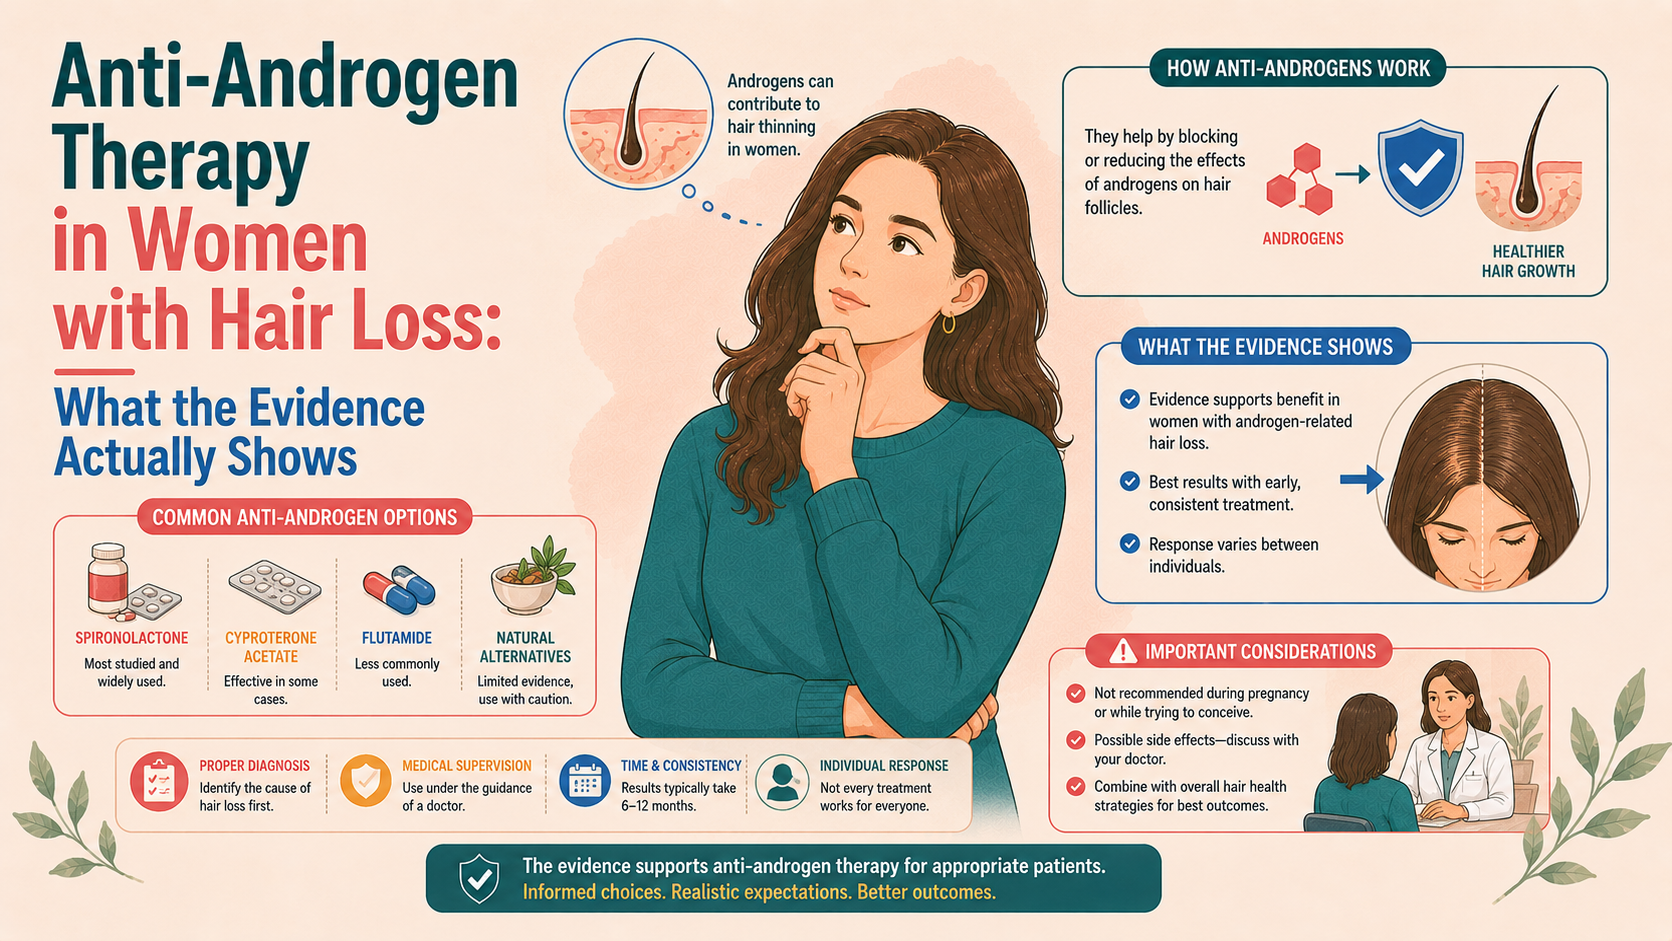
Minoxidil can support growth in suitable conditions. Finasteride and dutasteride reduce formation of DHT and can help selected people with pattern hair loss. These are different actions, with different risks and suitability.
Inflammatory and autoimmune conditions may need treatment directed at the immune process. A deficiency or thyroid disorder needs appropriate assessment and management. None of these problems can be diagnosed simply by choosing a product marketed for “hair health”.
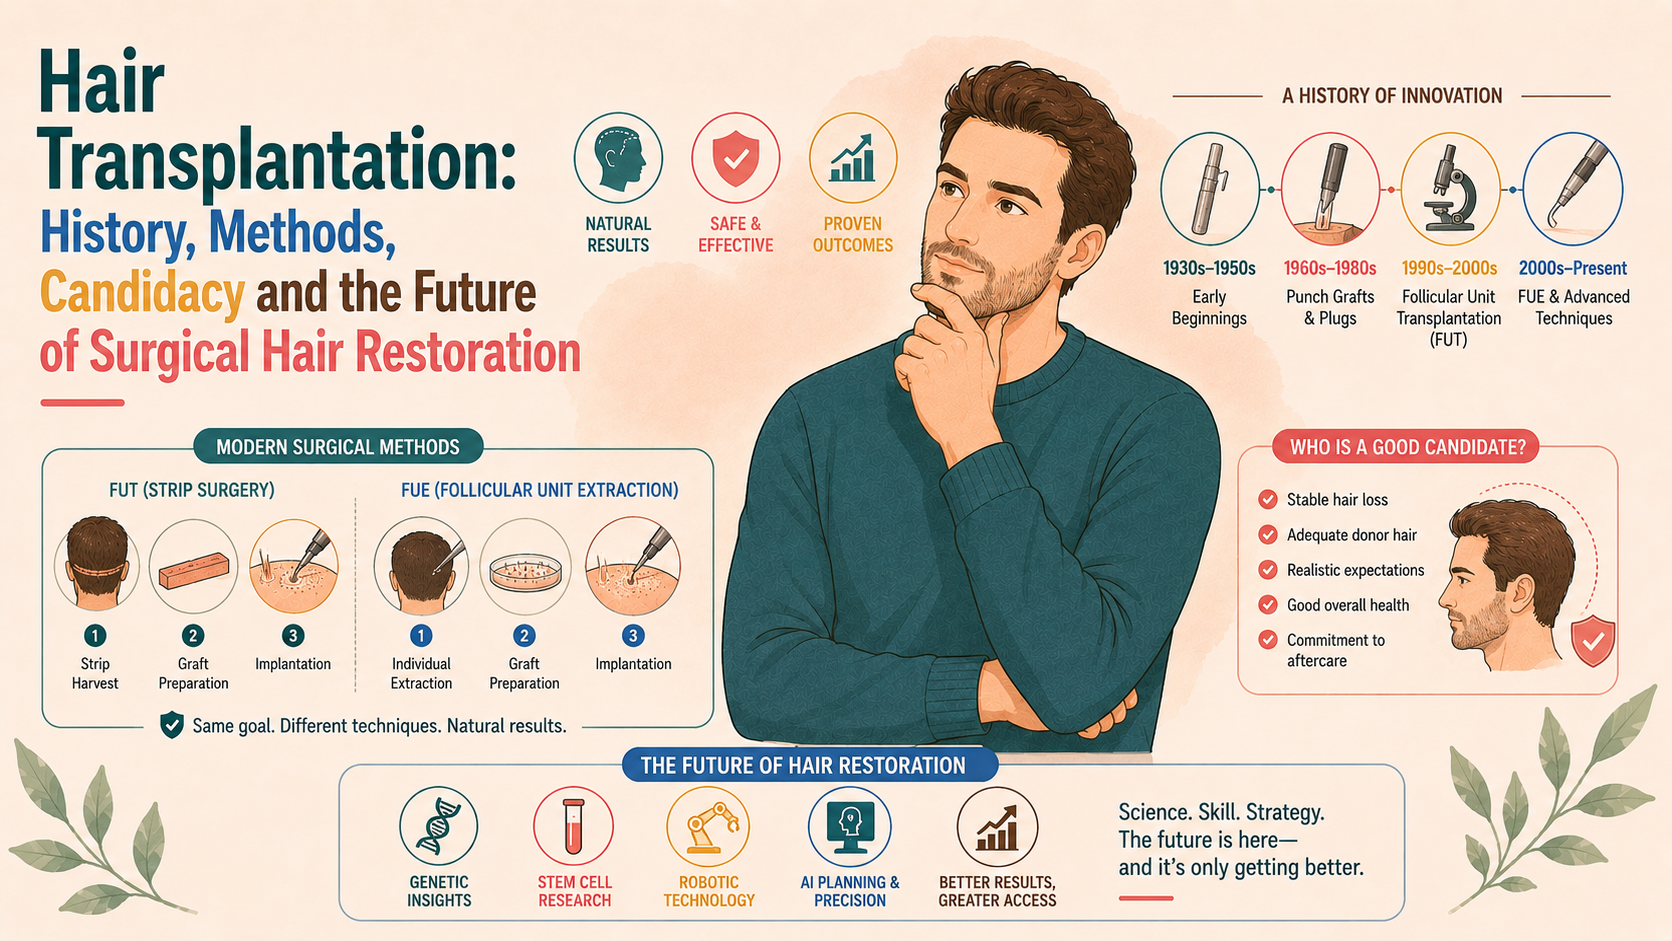
A transplant takes follicles from a suitable donor area and moves them. It does not create an unlimited supply or cure the tendency of surrounding hair to thin. Donor assessment matters because the back and sides are relatively resistant in many people, not guaranteed to be unaffected in everyone.
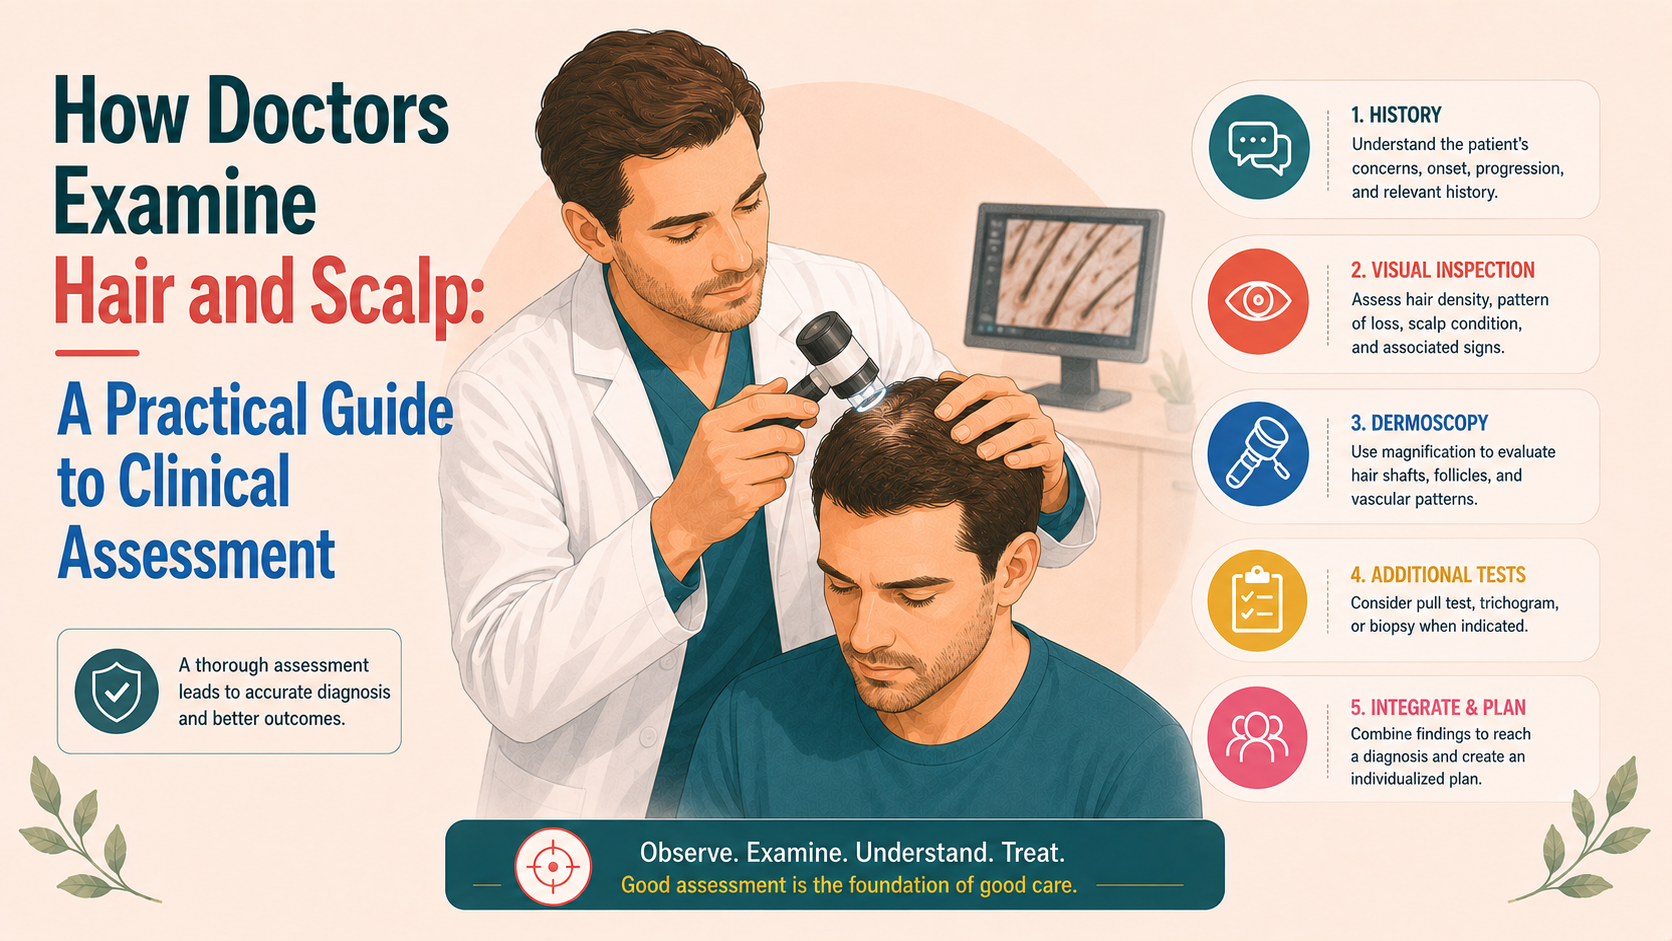
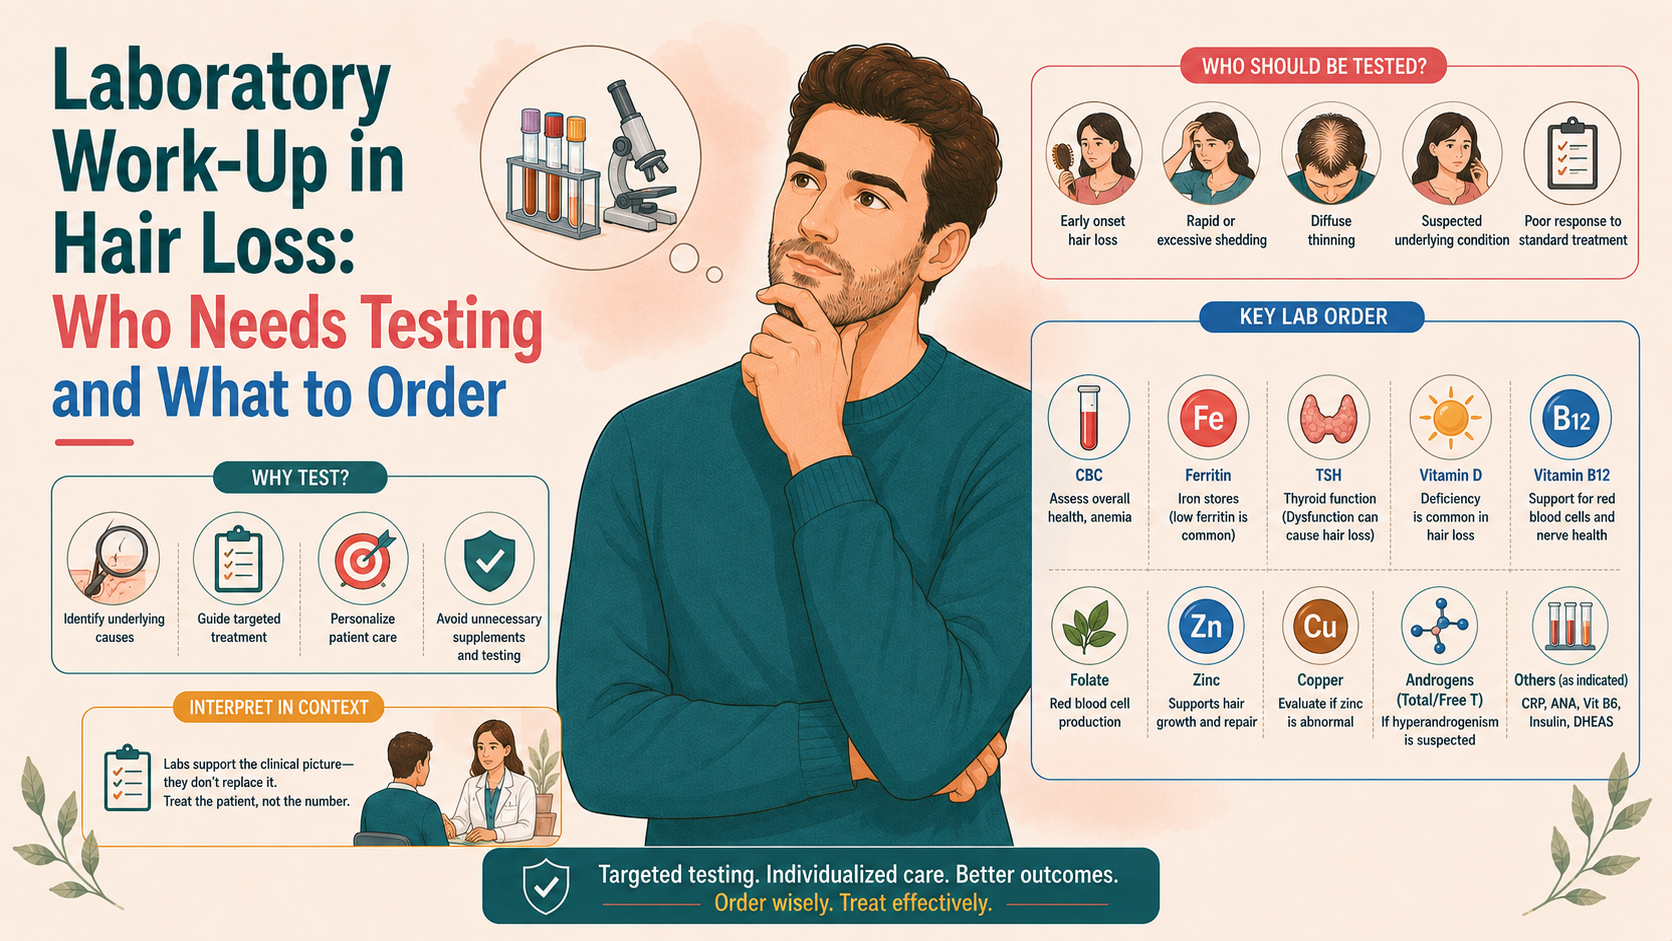
If you are noticing a persistent change, an assessment can separate shedding, miniaturisation, breakage and inflammation more reliably than repeated mirror checks. A clinician may use magnification, and sometimes targeted blood tests or a biopsy, depending on the findings.
Seek prompt assessment for rapid or patchy loss, especially with pain, inflammation or changes that might suggest scarring. You do not need to wait until hair loss is extensive to ask for help.
Once the diagnosis is clearer, the treatment discussion becomes more useful. You can ask what the proposed option is trying to change, what result is realistic and how you will assess whether it is helping.