Male and female pattern hair loss both involve progressively finer hair, but the hormonal biology, typical pattern and treatment evidence are not identical.


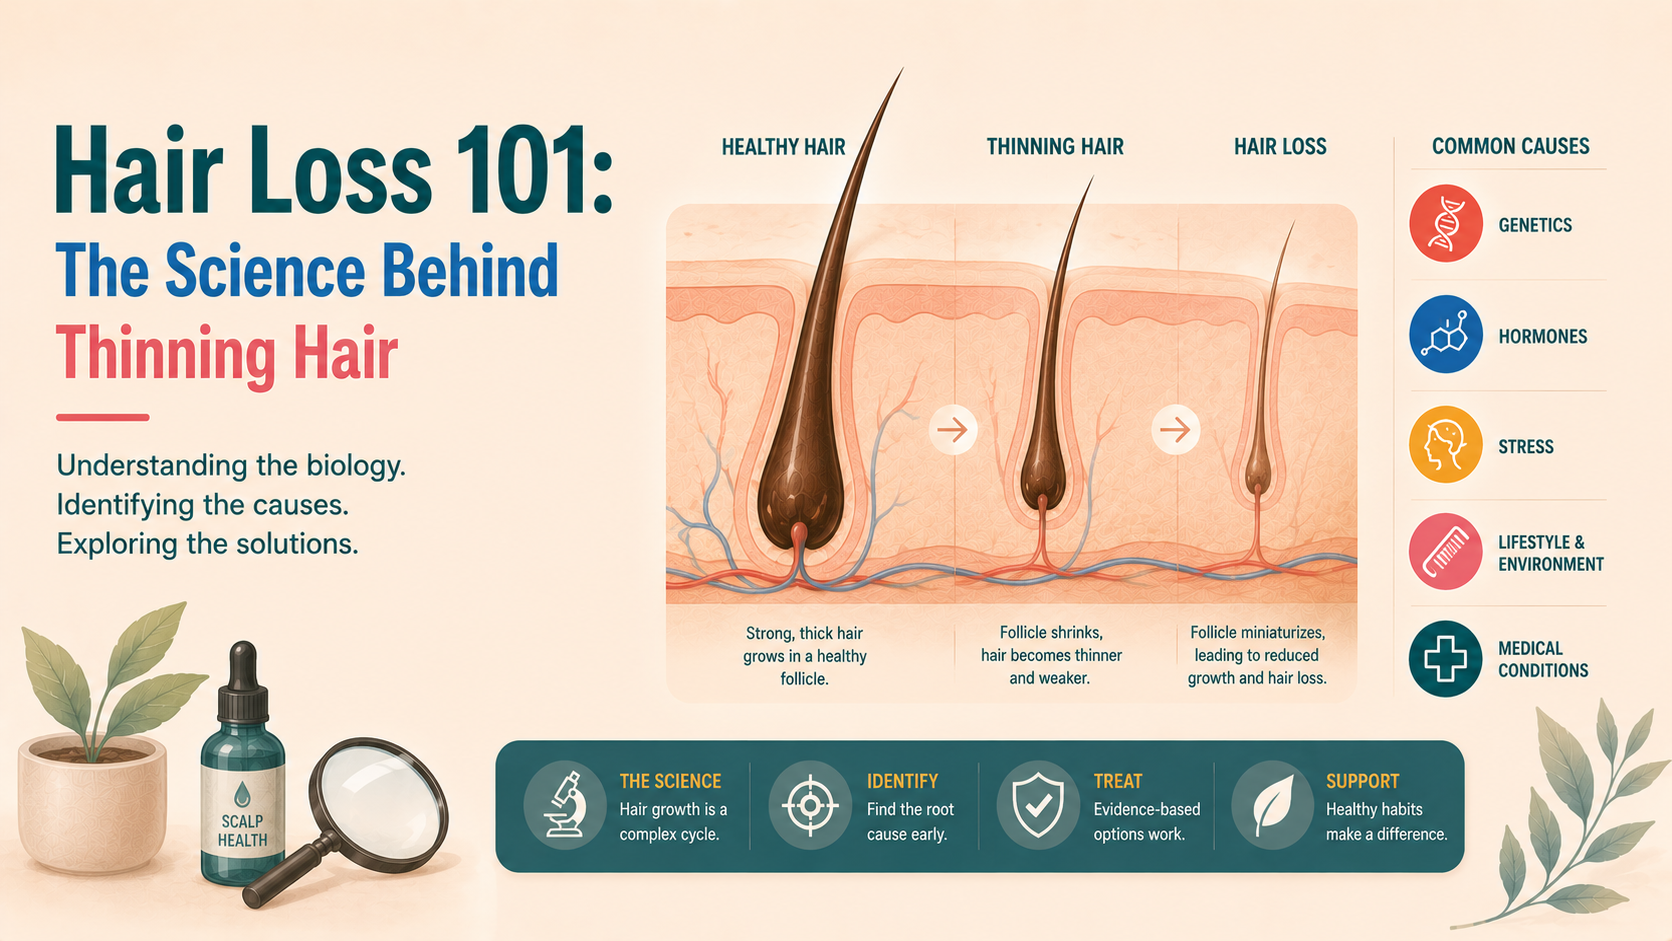
In pattern hair loss, affected follicles gradually produce finer, shorter hairs. The scalp becomes more visible even when hair is still growing. This is called miniaturisation, and it helps explain why someone can lose volume without noticing handfuls of hair falling out.
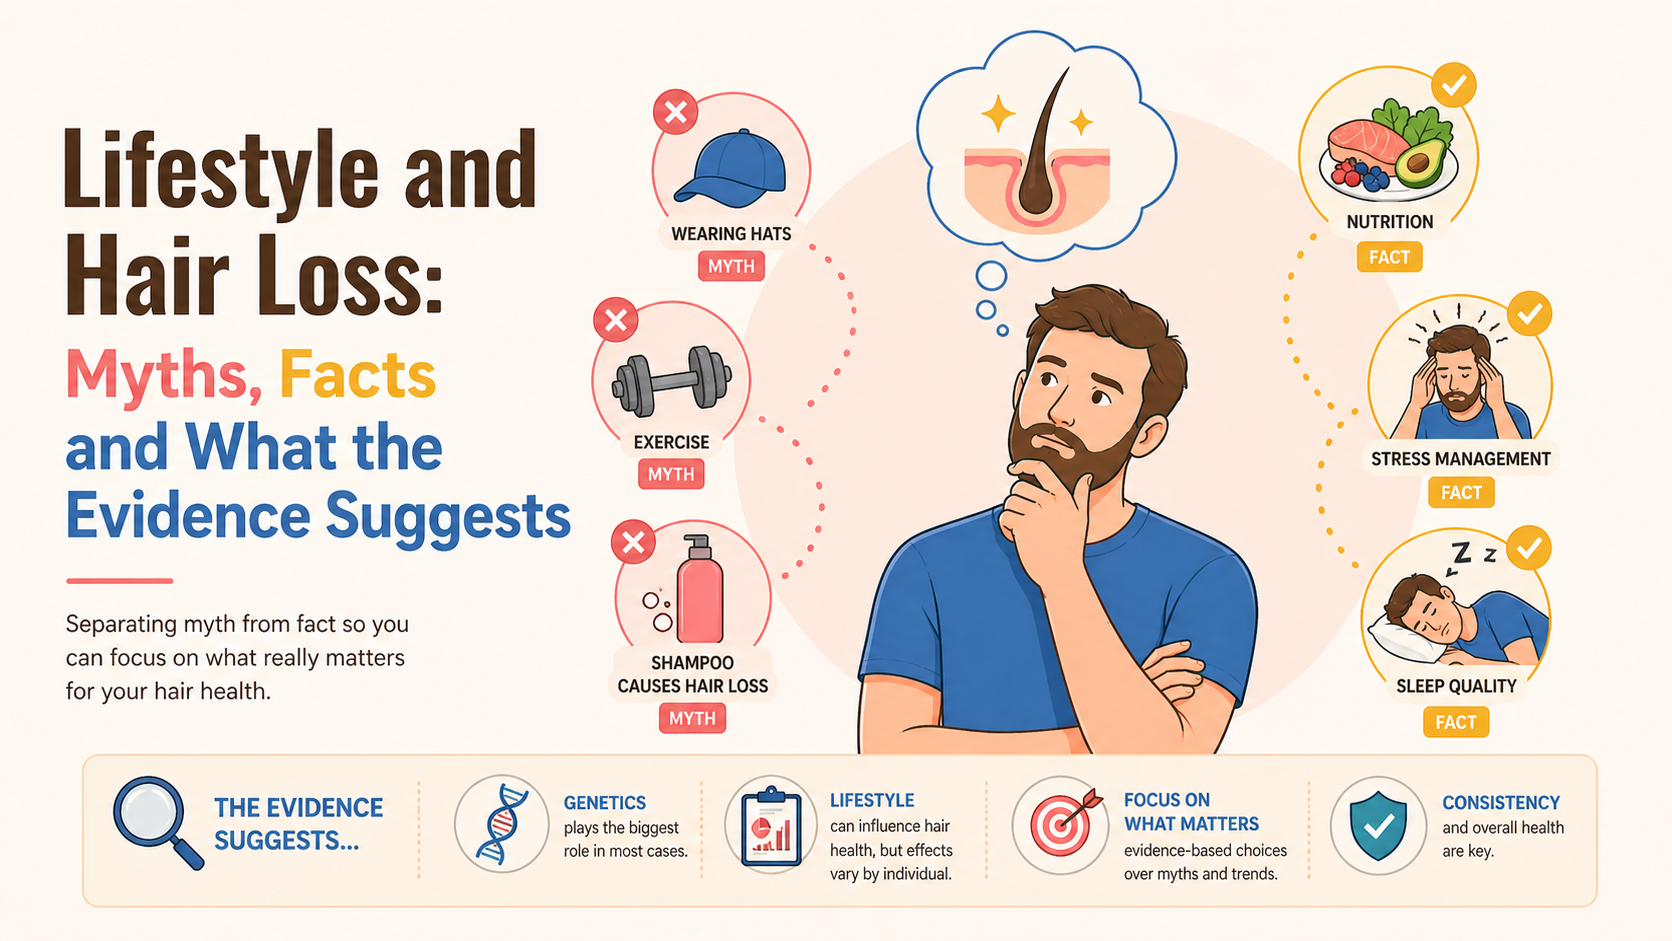
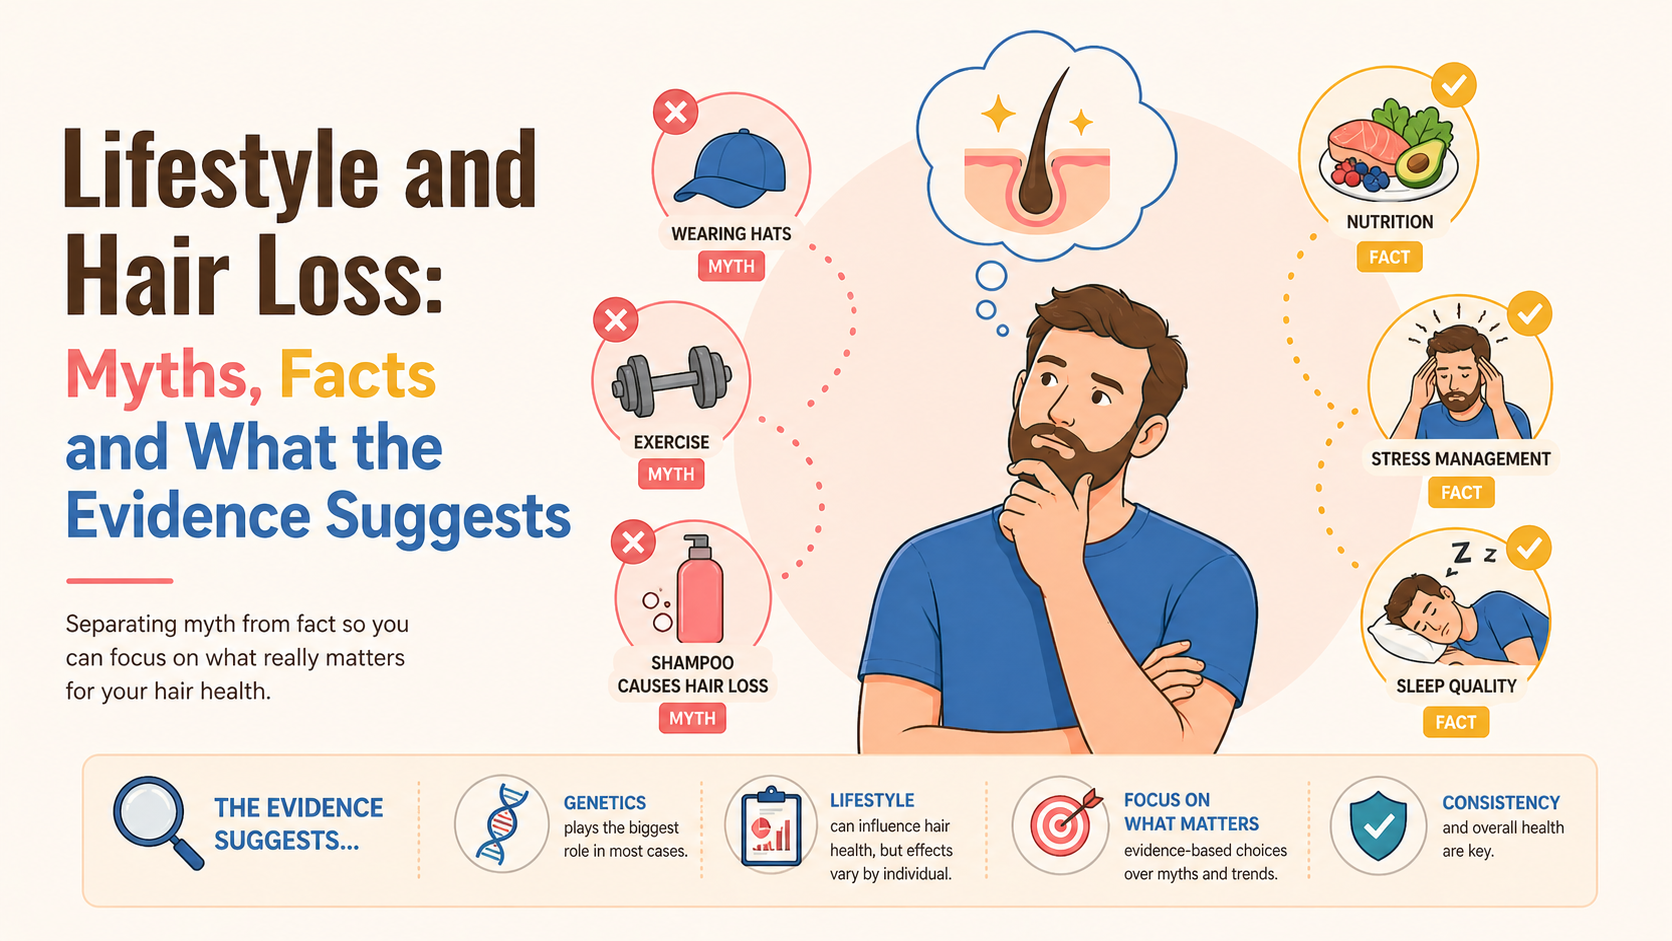
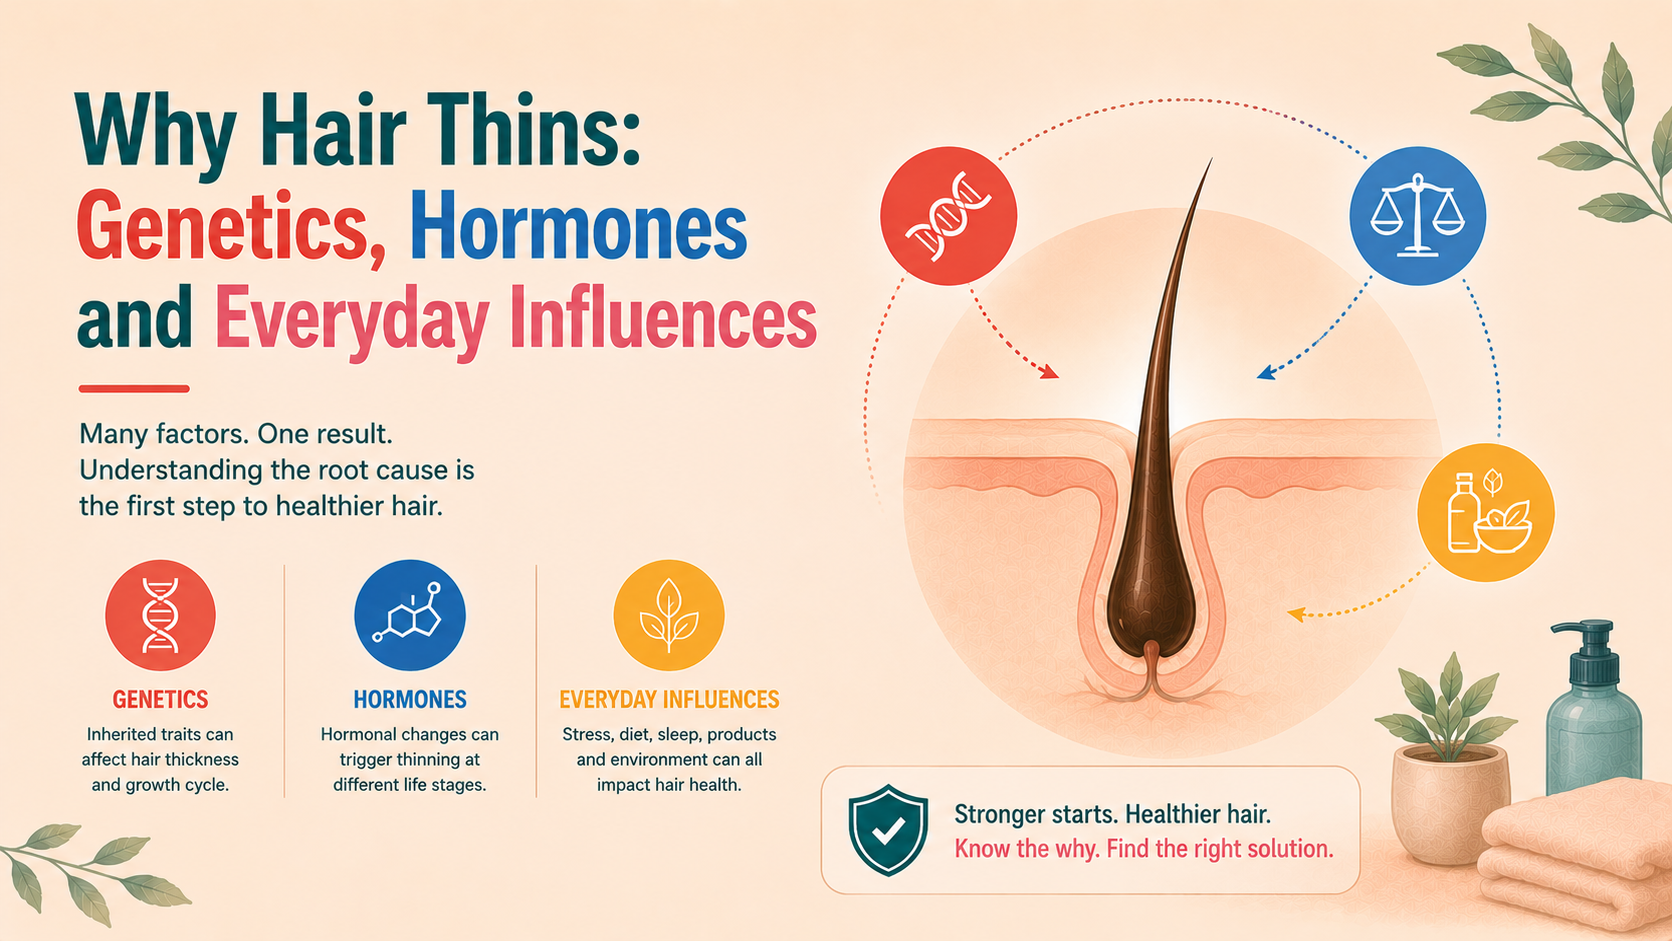
Genetics contribute in both men and women. Neither condition is explained by a single relative’s hairline, and neither is a sign that someone has failed to wash, eat or look after themselves properly.
Both can progress slowly enough to be difficult to judge day to day. Treatment usually works over months, and preserving existing coverage can be a worthwhile result even without dramatic regrowth.
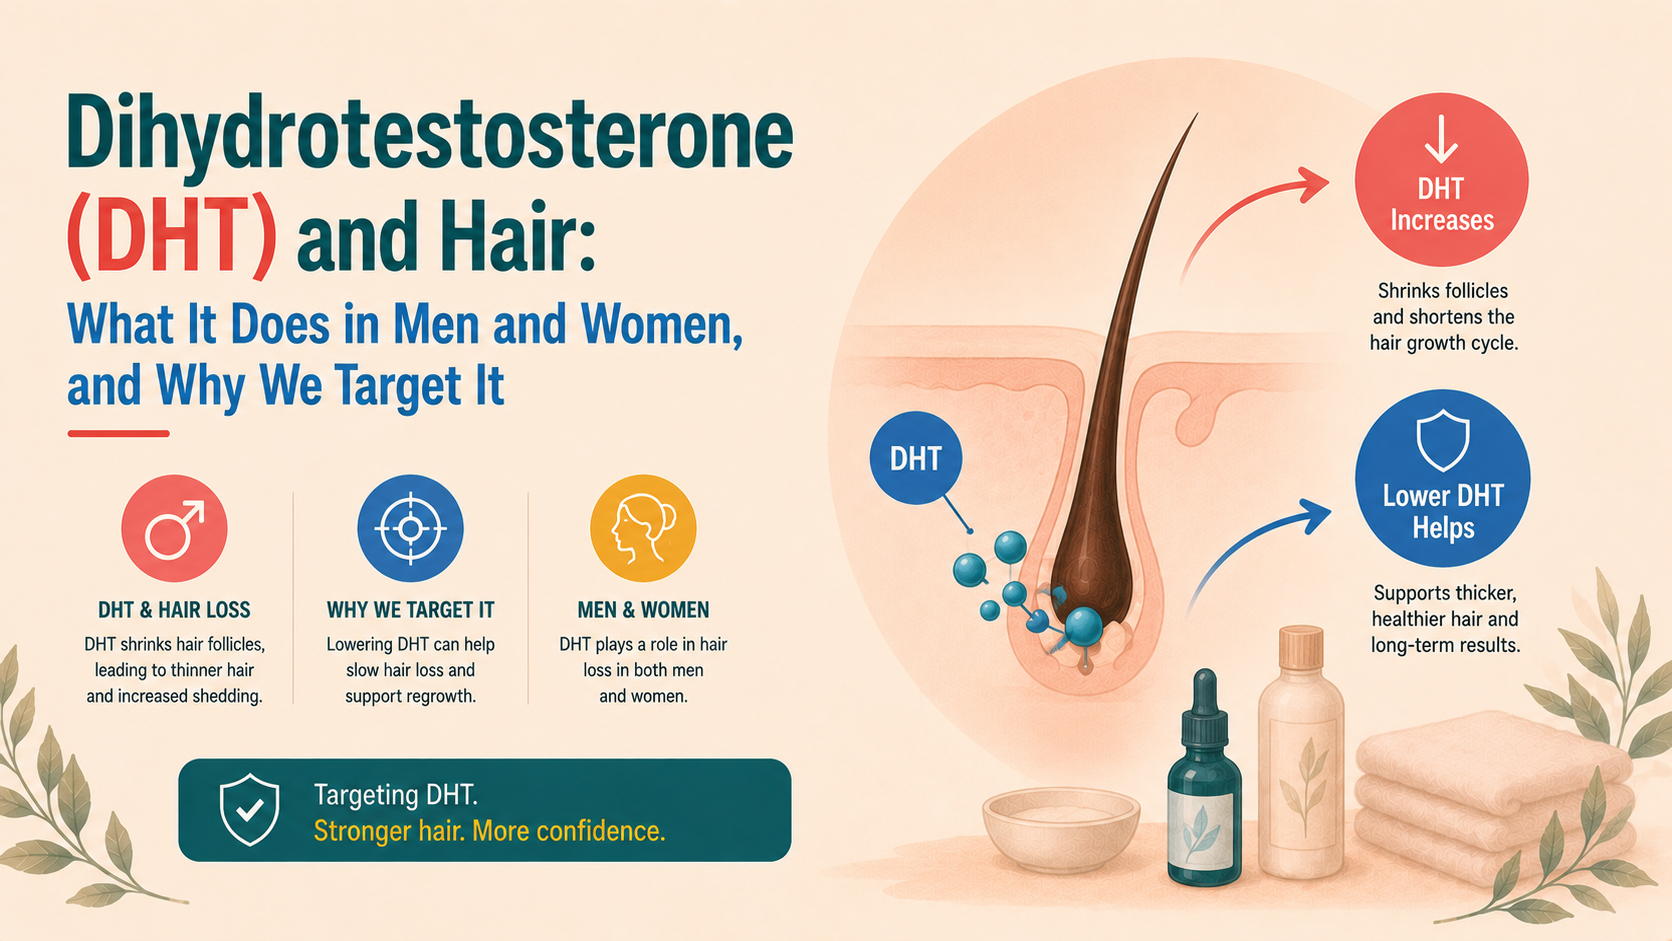
In male pattern hair loss, the role of DHT is well established. Susceptible follicles respond to androgen signalling by miniaturising over time. Most affected men do not have abnormally high testosterone; the response of the follicle matters.
Female pattern hair loss is more complex. Some women have androgen excess, but many do not, and not all cases appear to depend on androgens in the same way. Describing it as male baldness with less testosterone misses that uncertainty.
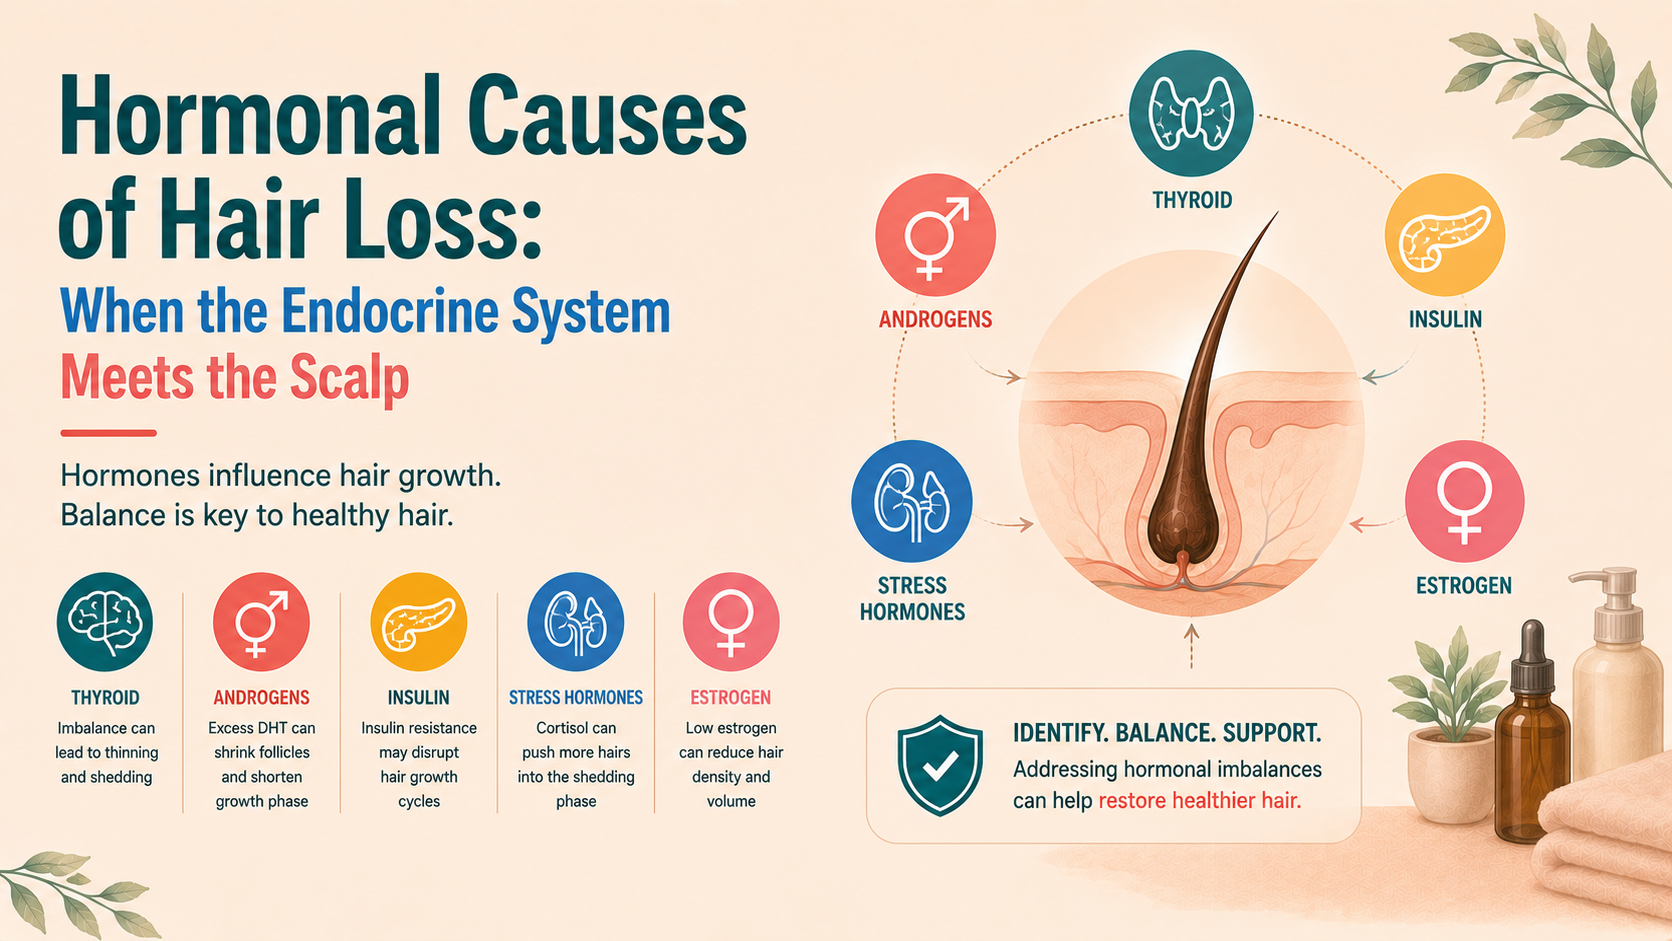
Periods, signs of androgen excess and the menopausal transition can provide useful context. Polyendocrine metabolic ovarian syndrome (PMOS), previously called PCOS, is one possible associated condition, but thinning hair by itself does not establish that diagnosis. A normal blood test does not rule out female pattern hair loss either.
Men commonly develop recession at the temples, thinning at the crown, or both. With progression, those areas can join. The hair around the back and sides is often relatively resistant, although it is not guaranteed to remain dense in every person.
Women more often notice a widening central parting, reduced volume or increased scalp visibility through the top of the hair. The front hairline is often retained. Advanced loss can still be substantial, even though the typical pattern differs from the familiar male horseshoe.
These are common patterns, not rules that every scalp must follow. Some men thin diffusely and some women develop more frontal recession. A change that does not fit the usual pattern is a reason to examine it carefully.
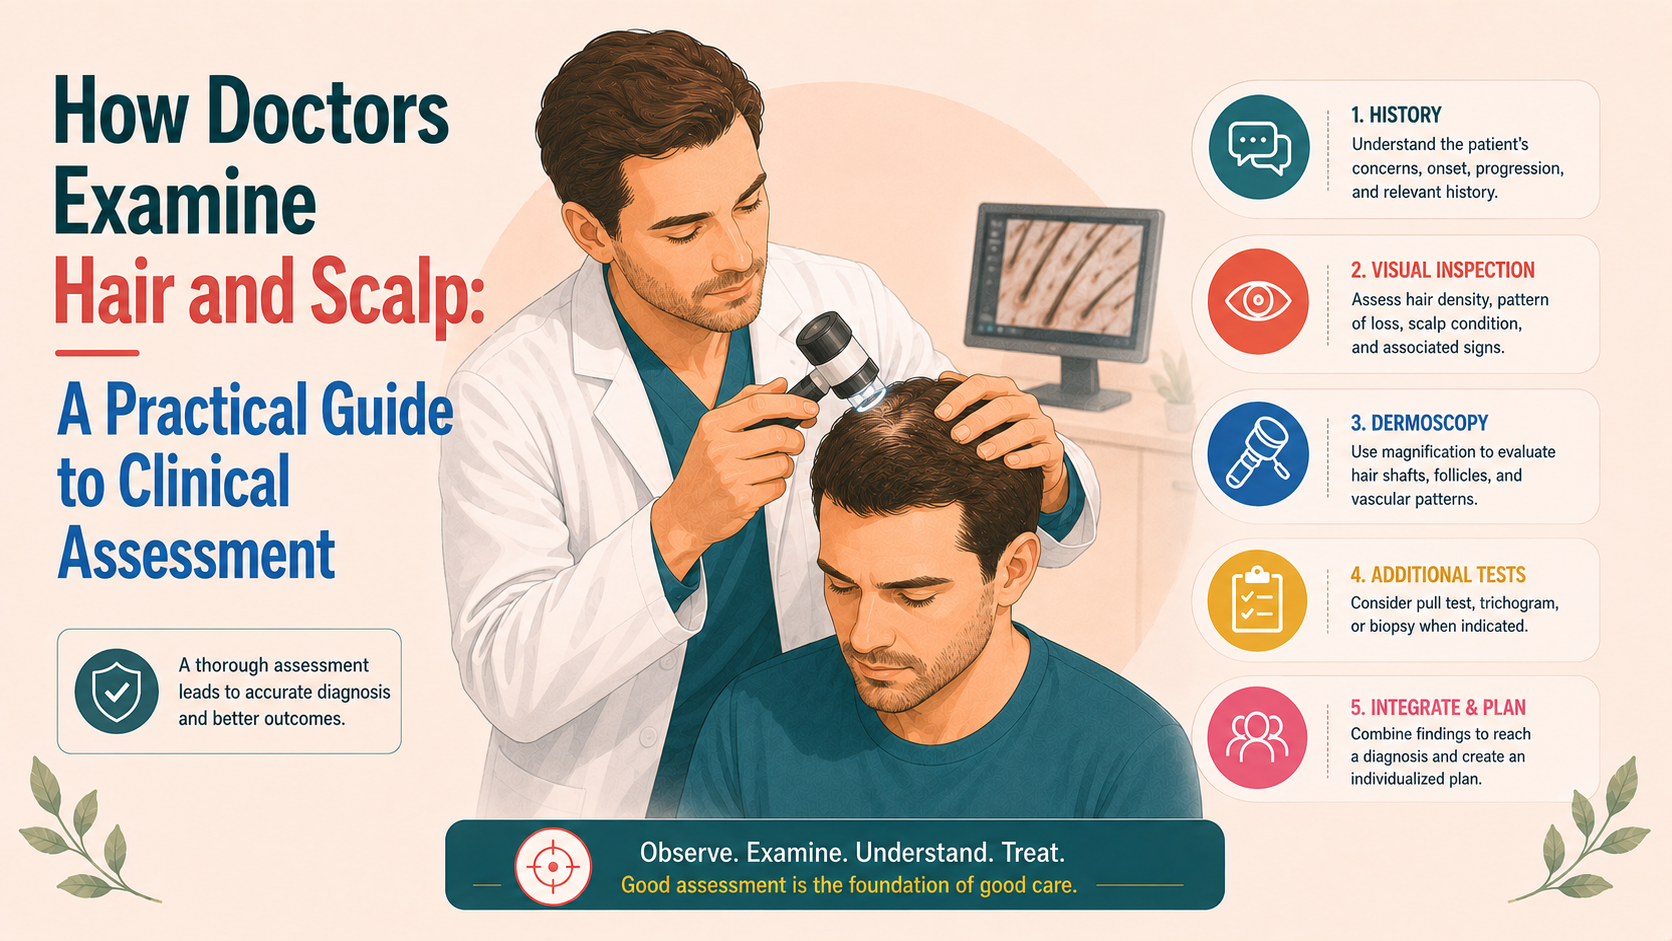
The useful starting questions are similar: when did the change begin, how quickly is it progressing, is there increased shedding, and does the scalp hurt, itch or look inflamed?
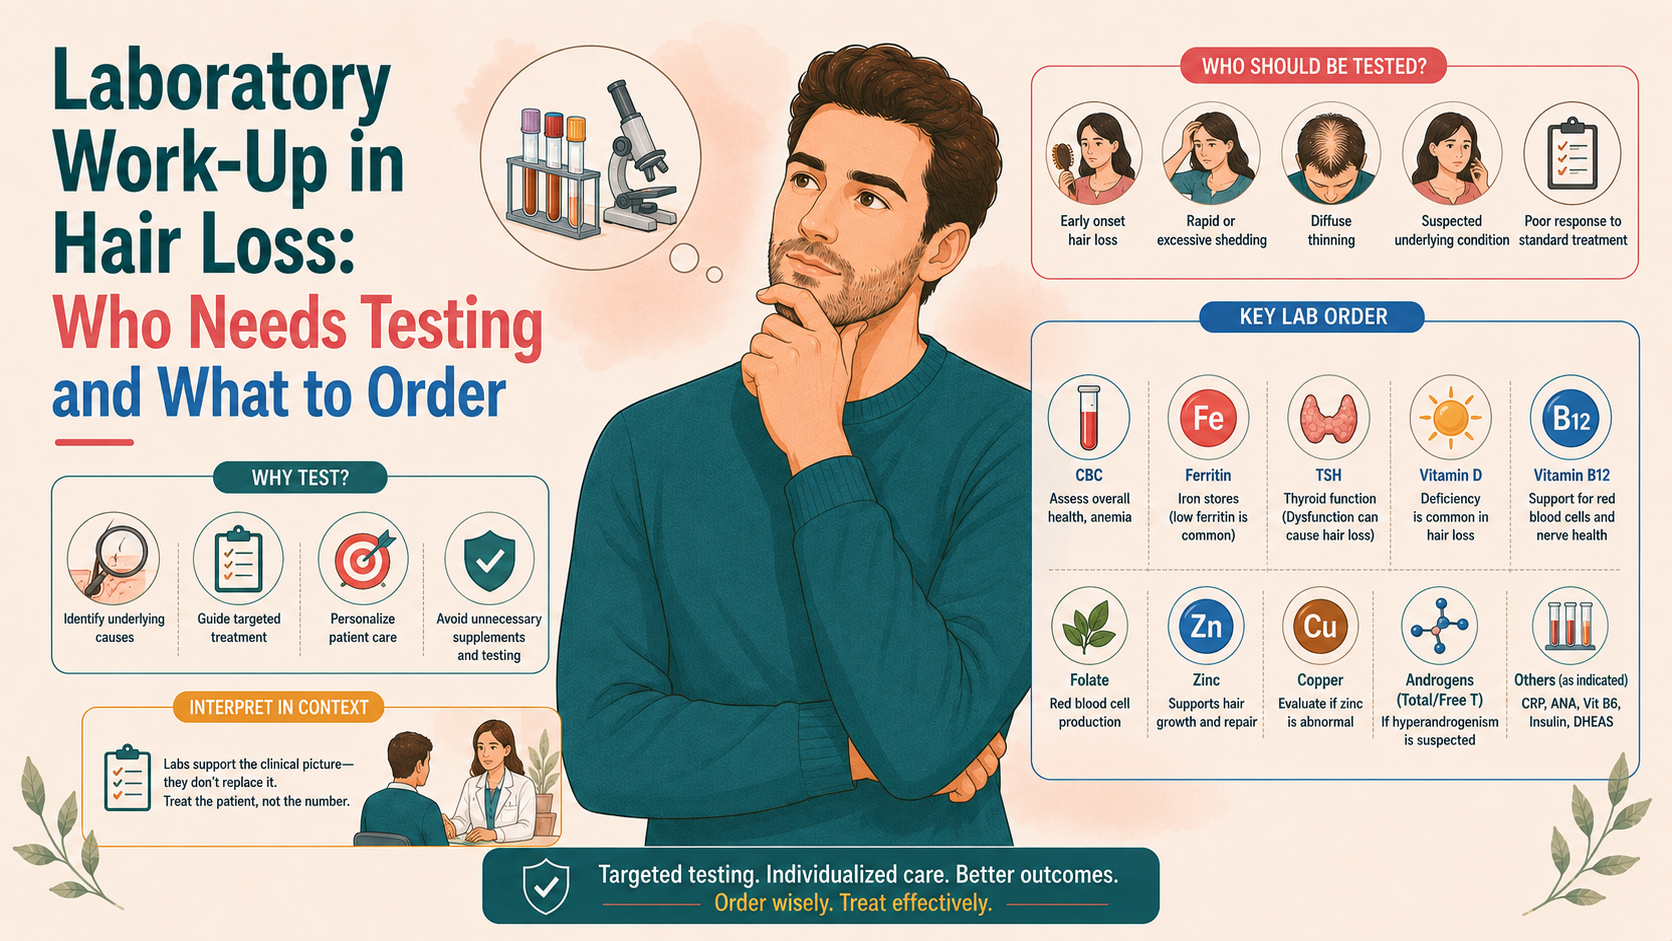
Trichoscopy, which magnifies the scalp and hairs, can help identify miniaturisation and signs of another condition. Blood tests are chosen when the history suggests a possible contributor, such as iron deficiency, thyroid disease or androgen excess. They do not replace looking at the scalp.
Telogen effluvium, alopecia areata and scarring disorders can affect either sex. Pattern hair loss can coexist with them. Being a young man with a receding hairline, or a woman near menopause with thinning hair, should not make every other possibility invisible.
Topical minoxidil has established uses in both men and women, although formulations and licensed schedules differ. Oral minoxidil is an off-label option for selected people and requires assessment of systemic risks.
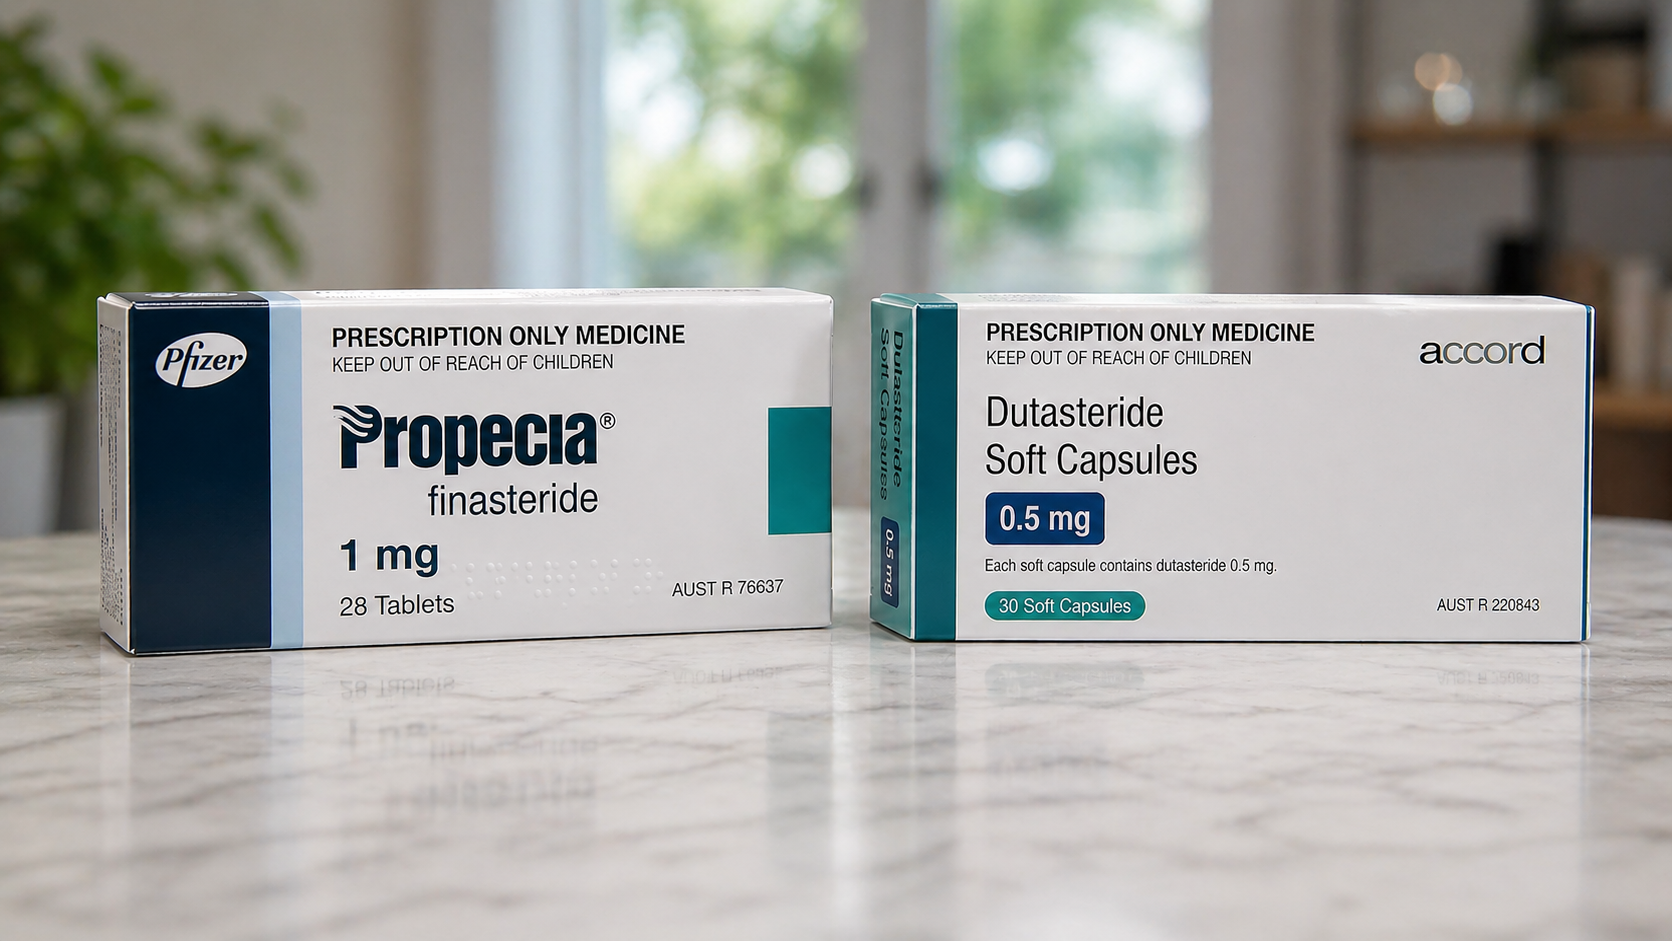
Finasteride has much stronger evidence in men than in women. Dutasteride is also used for male pattern hair loss, with licensing varying by country. Both require a discussion of sexual and mood-related adverse effects. Their use in women is more selective, with pregnancy risk a central concern.
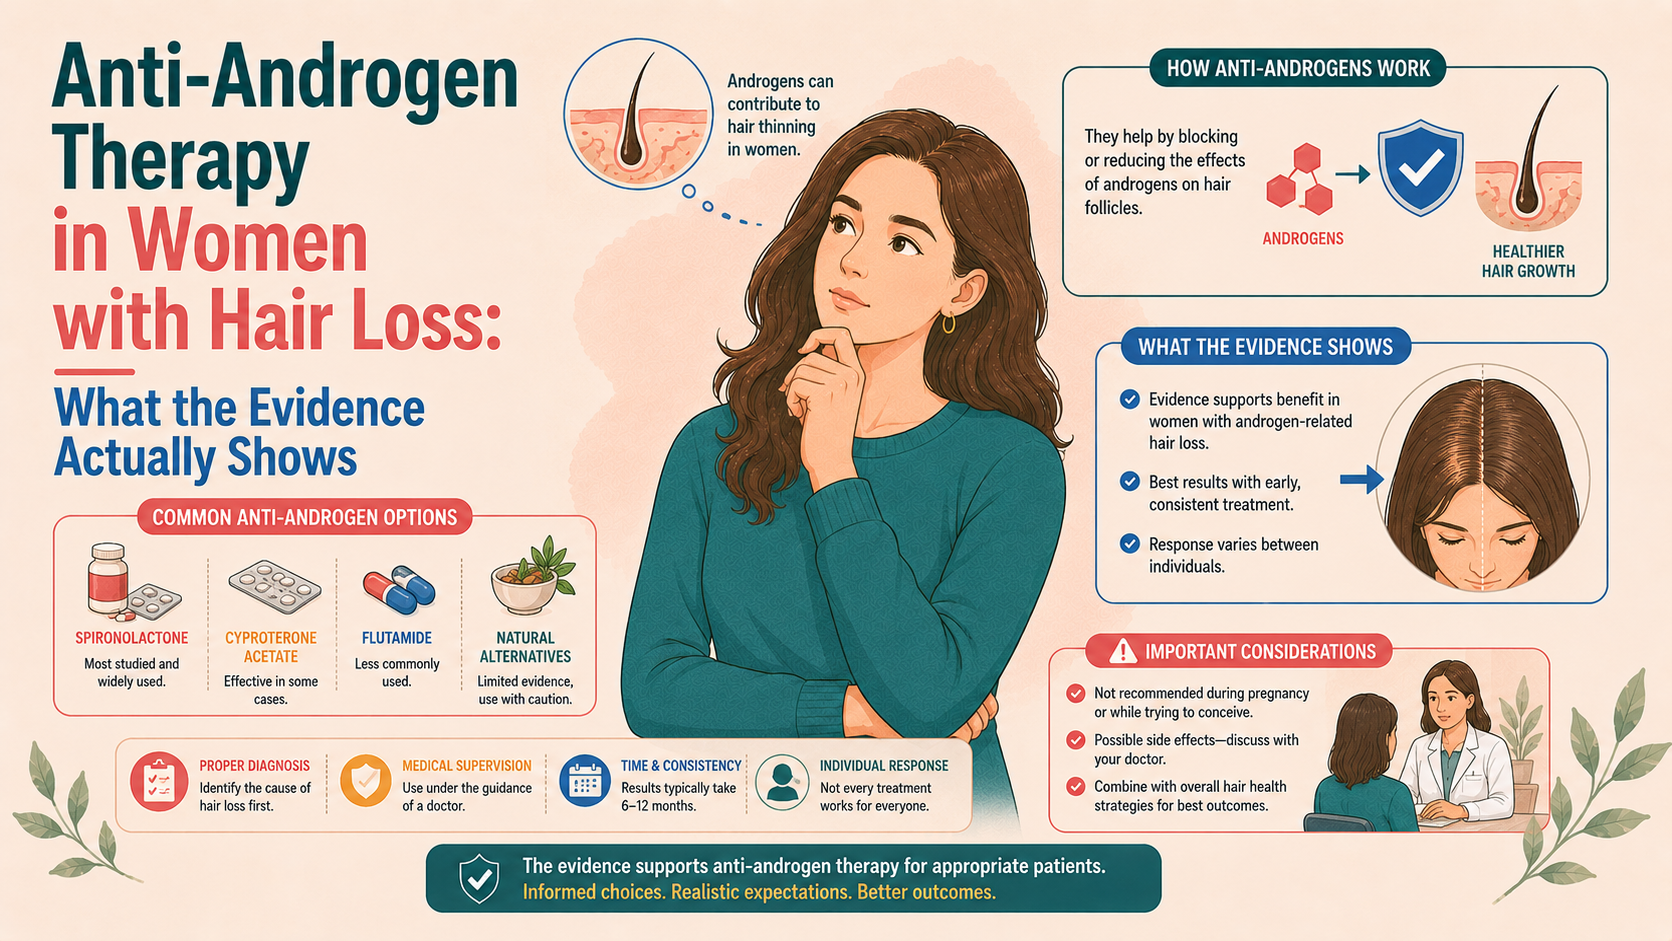
Spironolactone is a common off-label option in women. Its suitability depends on medical history, pregnancy plans, other medicines and the expected benefit. Normal androgen levels do not automatically settle that decision.
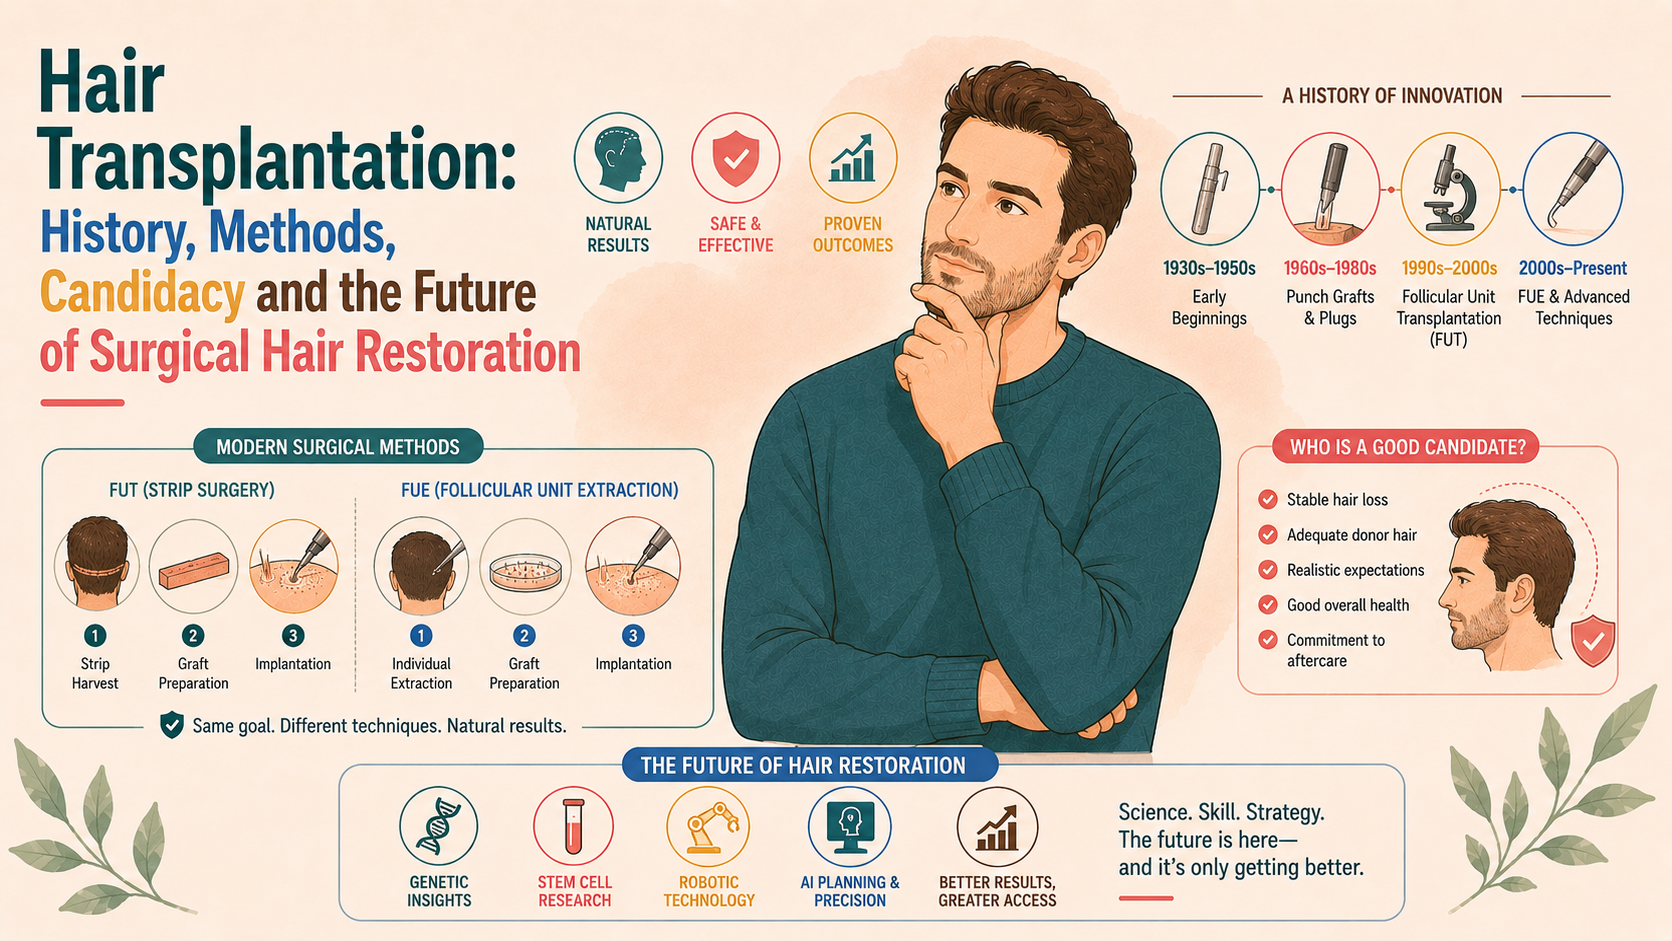
Procedures need the same care in interpretation. A study of microneedling in men does not prove equal benefit in women. A transplant also requires suitable donor hair, which can be harder to identify when thinning is diffuse.
I can speak from experience about being a man who worries about his hair. I cannot claim to know from the inside what it is like for a woman whose hair loss is repeatedly overlooked or dismissed.
At the same time, the visible amount of hair loss is a poor measure of its emotional cost. Someone with mild thinning may spend hours concealing it, while someone with advanced loss may feel comfortable with their appearance.
There is no useful competition over who has it worse. Good care takes the diagnosis seriously and also asks how much attention, confidence or freedom the problem is taking from the person living with it.